My PSA Is High—Do I Have Prostate Cancer, and What Tests Should I Do Next?
Seeing “PSA high” on a blood report can be frightening. The first fact to remember is that a raised PSA is not the same as a prostate-cancer diagnosis. PSA is made by prostate tissue, so benign enlargement, inflammation and infection can also raise it. Conversely, some prostate cancers occur with a PSA that is not dramatically elevated.
The useful question is not simply “Is my PSA normal?” but “What does this PSA mean for me, and what should happen next?” Interpretation depends on age, prostate size, symptoms, previous PSA values, medicines, family history, examination and imaging.
Quick answer
- A high PSA can occur without cancer.
- A repeat PSA may be appropriate after temporary causes are addressed.
- Multiparametric MRI helps assess risk and target a biopsy.
- Only tissue from a biopsy can confirm most prostate-cancer diagnoses.
- If cancer is found, treatment ranges from active surveillance to surgery, radiotherapy or systemic therapy.
What is PSA?
Prostate-specific antigen is a protein produced by prostate cells. A small amount normally enters the bloodstream. The value is continuous: risk generally rises as PSA rises, but there is no universal number that proves or excludes cancer.
Why can PSA rise without cancer?
- Benign prostatic hyperplasia (BPH): a larger prostate can produce more PSA.
- Prostatitis or urinary infection: inflammation may cause a temporary rise.
- Urinary retention: an overfilled bladder and acute obstruction can affect PSA.
- Recent urinary procedures: catheterisation, cystoscopy or prostate manipulation may matter.
- Natural variation: laboratory and biological changes mean one result should not always be read in isolation.
Tell your clinician about fever, burning urination, retention, recent procedures and medicines. Do not take antibiotics merely to lower PSA unless infection is actually suspected and assessed.
Step 1: confirm the result in context
For a moderately raised PSA and a non-suspicious examination, guidelines may support repeating the test after several weeks under standardized conditions. Your doctor may request urine testing and treat a confirmed infection first. An urgent pathway may be needed when PSA is very high, examination is suspicious, symptoms suggest advanced disease or imaging already shows concern.
Bring every previous PSA report. PSA trend can be more informative than a single number, although velocity alone should not dictate biopsy.
Step 2: clinical examination and risk assessment
A urologist reviews urinary symptoms, family history—especially prostate, breast or ovarian cancer—ethnicity, age and general health. A digital rectal examination checks prostate texture and possible nodules. A normal examination does not completely rule out cancer; an abnormal one increases concern.
Tests that may refine risk
- Free-to-total PSA: may help in selected borderline cases.
- PSA density: PSA divided by prostate volume.
- Prostate Health Index or other biomarkers: availability and usefulness vary.
- Multiparametric MRI: maps suspicious lesions and prostate volume.
Step 3: multiparametric prostate MRI
MRI assigns suspicious areas a PI-RADS score and helps plan targeted biopsy. A higher score generally means greater concern, but MRI is not a yes-or-no cancer test. Image quality and specialist radiology interpretation matter. A low-suspicion MRI may support monitoring in some men; others still need biopsy because of PSA density, family history or clinical findings.
Step 4: when is a prostate biopsy needed?
A biopsy samples tissue for a pathologist to determine whether cancer is present and, if so, its Grade Group. Modern pathways often combine targeted cores from MRI-visible lesions with systematic sampling. Transperineal biopsy passes needles through the skin between the scrotum and anus and may reduce infection risk compared with the transrectal route, although local practice and patient factors differ.
Ask about anaesthesia, antibiotic policy, blood-thinner management, urine infection testing, bleeding, retention and when results will be available.
If cancer is found, what happens next?
The report is interpreted with PSA, MRI, clinical stage and sometimes PSMA PET/CT or other staging scans. Broad pathways include:
- Active surveillance for suitable low-risk disease;
- Radical prostatectomy, including robotic surgery, for selected localized cancers;
- Radiotherapy with or without hormonal treatment;
- Systemic treatment for disease that has spread;
- Watchful waiting when symptom control is more appropriate than curative treatment.
The “best” option is the one matched to cancer risk, life expectancy, urinary function, sexual priorities and personal values—not automatically the most aggressive treatment.
Questions to ask at your appointment
- Could infection, retention or prostate size explain this result?
- Should I repeat PSA, and how should I prepare?
- What are my PSA density and MRI findings?
- Do I need a biopsy, and will it be MRI-targeted?
- If cancer is found, is active surveillance safe for my risk group?
- How would each treatment affect urination, continence, erections and follow-up?
How Dr. Jamal Azmi can help
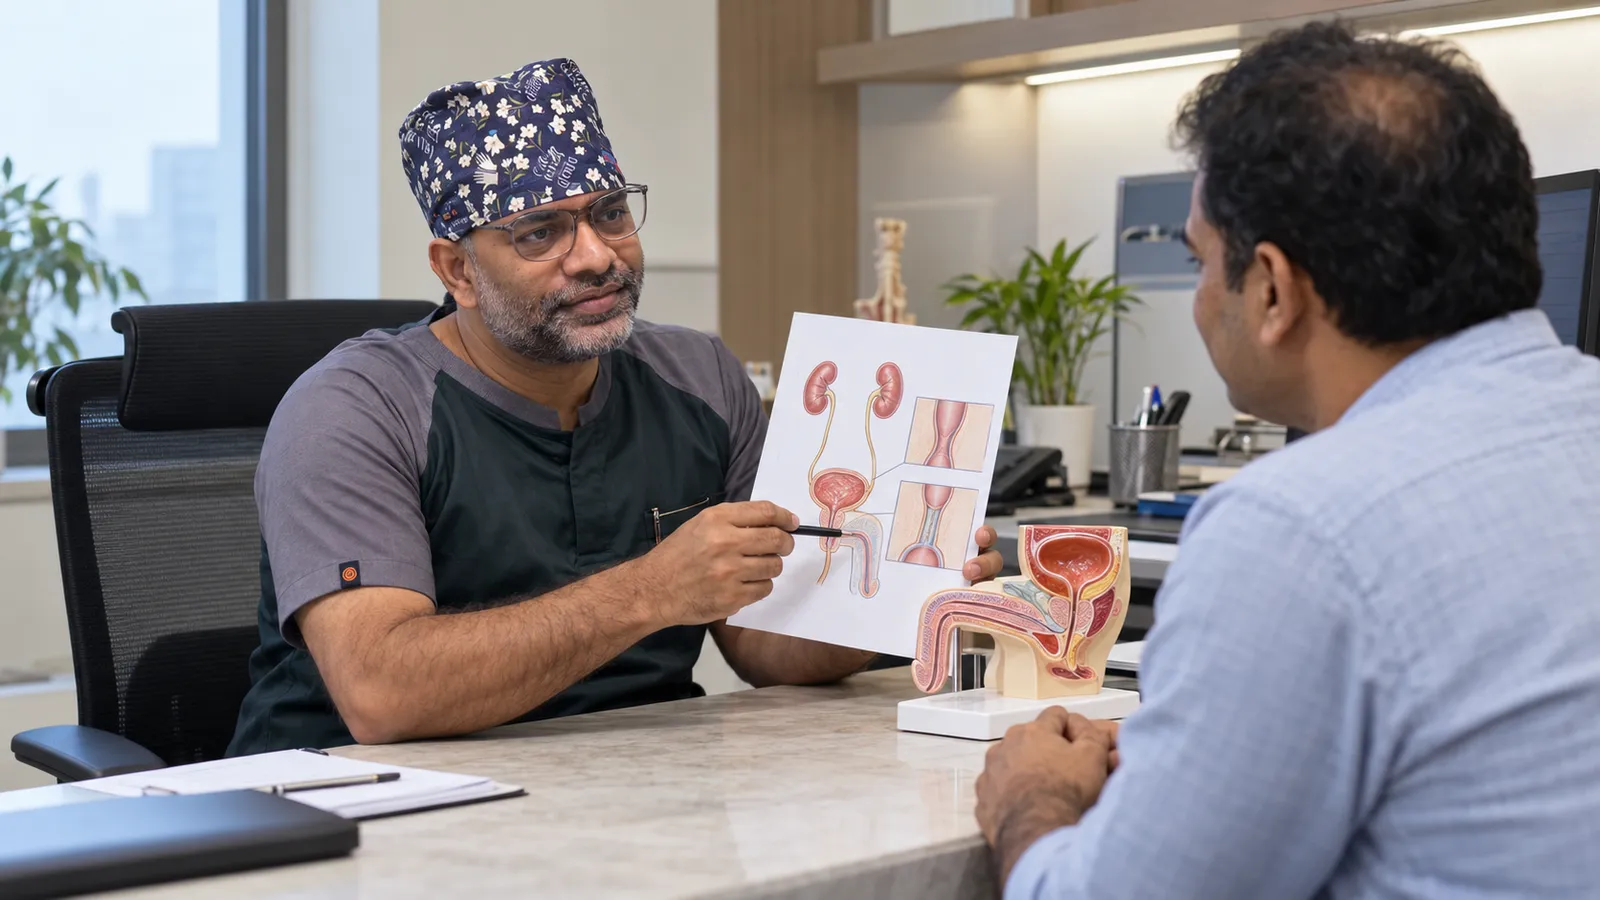
Dr. Jamal Akhtar Azmi provides evaluation of raised PSA, prostate MRI review, biopsy planning and uro-oncology counselling in Mumbai. When surgery is appropriate, his practice includes robotic radical prostatectomy. Patients can also discuss non-surgical alternatives and multidisciplinary review.
Learn about prostate cancer evaluation and treatment
Medical references
- EAU Prostate Cancer Guidelines: Diagnostic Evaluation
- Urological Society of India prostate-cancer guidelines
Last medically reviewed: 31 October 2026. Seek urgent care for inability to urinate, severe pain, fever, confusion or rapidly worsening illness.
Raised PSA and Prostate Cancer
Frequently Asked Questions
Does a high PSA always mean prostate cancer?
No. PSA can rise because of benign prostate enlargement, prostatitis, urinary infection, recent instrumentation and other factors. PSA is prostate-specific, not cancer-specific. The result must be interpreted with age, symptoms, examination, prostate volume, trend and other tests.
Should an elevated PSA test be repeated?
A repeat test is often considered for a moderately elevated result when there is no urgent clinical concern. The timing and preparation should be decided by a clinician, particularly if infection, urinary retention, recent catheterisation or another temporary influence is possible.
Do I need an MRI before a prostate biopsy?
Multiparametric MRI is commonly used before biopsy to identify suspicious areas, estimate local risk and guide targeted sampling. MRI does not replace all biopsies, and a normal MRI does not make the risk zero. The complete clinical picture determines the next step.
What is PSA density?
PSA density divides the PSA level by prostate volume, usually measured on ultrasound or MRI. It helps distinguish a PSA rise related to a large benign prostate from a result that may deserve closer investigation, but it is not used alone to diagnose cancer.
If prostate cancer is found, will I need surgery immediately?
Not always. Low-risk localized cancers may be suitable for active surveillance. Other cases may need surgery, radiotherapy, hormonal treatment or combined care. Grade group, stage, PSA, imaging, age, health and patient preferences all matter.
When is robotic prostatectomy considered?
Robotic radical prostatectomy may be considered for selected patients with clinically localized or locally advanced prostate cancer when surgery is appropriate. Cancer control, continence, sexual function, medical fitness and alternatives should be discussed with a uro-oncology team.